Mood Changes on Spironolactone: Separate Acne Outcomes From Drug Effects
A mood change after starting spironolactone deserves attention. Timing helps investigate it, but timing alone cannot establish that the medicine caused it. Acne itself can affect emotional well-being, and changes in sleep, health, stress, or other medicines can occur during treatment.
The useful distinction is between improvement in acne-related quality of life and evidence that a drug causes a psychiatric condition. Research supports spironolactone as an acne treatment. It does not provide a reliable acne-specific rate of depression or anxiety caused by spironolactone.
What the evidence actually measures
The American Academy of Dermatology’s 2024 acne guideline overview recommends systemic spironolactone as a treatment option. That recommendation addresses acne treatment; the overview does not establish a psychiatric screening schedule.[2]
The SAFA randomized trial enrolled 410 adult women with facial acne lasting at least six months that clinicians judged suitable for oral antibiotics: 201 received spironolactone and 209 placebo. Its primary analysis included 342 participants, split 176 and 166.[3]
The study used 50 mg daily through six weeks, then 100 mg through week 24. This was a research protocol, not a personal dosing recommendation. The primary outcome was the Acne-QoL symptom subscale at week 12: a 0–30 scale where higher scores mean better acne-related outcomes.[3]
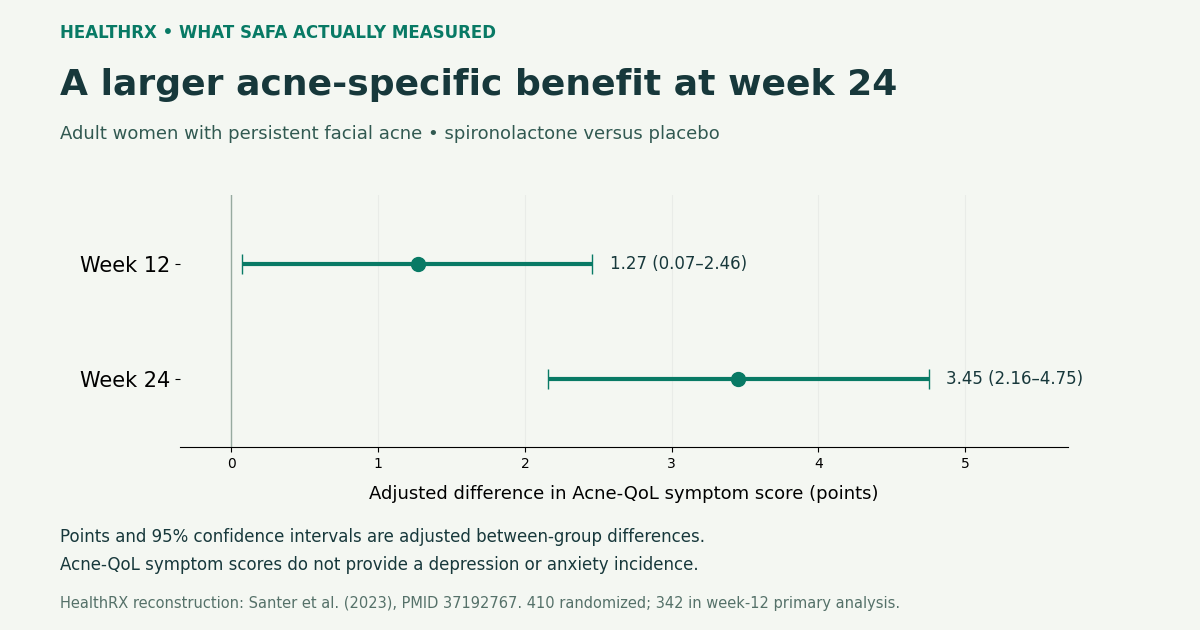
The adjusted between-group difference favored spironolactone by 1.27 points at week 12 (95% confidence interval 0.07–2.46) and 3.45 points at week 24 (2.16–4.75). These are scale points, not percentages or depression scores. They show a greater acne-related benefit over time, not proof of an antidepressant effect.[3]
Adverse reactions were slightly more common with spironolactone. Headaches were reported by 20% versus 12% with placebo (P=0.02). No serious adverse reactions were reported, but that does not establish zero risk or a clinical incidence of mood disorders.[3]
| Evidence and source | Question it helps answer | Limit of the answer |
|---|---|---|
| Randomized SAFA acne trial [3] | Does spironolactone improve acne-related symptoms compared with placebo? | Its Acne-QoL symptom outcome is not a psychiatric diagnosis or depression scale. |
| Meta-analysis of 42 heterogeneous studies [4] | Is acne associated with depression and anxiety? | Association cannot establish drug causation or predict an individual’s recovery. |
| Prescribing label: trial and postmarketing reports [1] | Which neurologic symptoms and medication risks are recognized? | Reports do not supply reliable acne-specific mood-change frequencies. |
| AAD guideline overview [2] | Is spironolactone a recommended systemic acne option? | A treatment recommendation does not answer whether a particular mood change is drug-related. |
Acne improvement and emotional improvement are different outcomes
A meta-analysis of 42 studies found associations between acne and depression (r=0.22, 95% confidence interval 0.17–0.26) and anxiety (r=0.25, 0.19–0.31). The studies were heterogeneous, so those averages cannot predict how any one person will feel.[4]
Clearing acne may ease appearance-related distress or make social activities more comfortable. Depression or anxiety may nevertheless persist, especially when other contributors are present. Conversely, someone can develop new emotional symptoms while their skin improves. Neither pattern alone settles whether spironolactone is responsible.
Track skin and mood separately. If acne improves but functioning worsens, the acne result should not obscure the need for a mental health assessment.
What the label can—and cannot—tell you
The label lists lethargy, mental confusion, ataxia, dizziness, headache, and drowsiness. Ataxia means impaired coordination. Clinical-trial and postmarketing reports do not reliably establish frequency or causality for every reaction, and they do not provide controlled acne-specific depression or anxiety rates.[1]
Dehydration, low blood pressure, kidney problems, and electrolyte changes can matter when assessing symptoms; none should be assumed from fatigue or low mood alone. The label also warns that spironolactone reduces lithium’s renal clearance, increasing toxicity risk, and calls for periodic lithium monitoring.[1]
Medication review should include ACE inhibitors, ARBs, NSAIDs, heparin, trimethoprim, and other potassium-raising medicines. Antidepressant compatibility needs an individual review rather than a blanket statement about SSRIs.[1]
Build a timeline that helps your prescriber
Record when symptoms started, their persistence, and their effect on ordinary life. Include medication changes even when they seem unrelated. A clear timeline can guide assessment without requiring you to prove the cause yourself.
| What to track | Useful details to bring |
|---|---|
| Acne | Changes in breakouts, discomfort, and appearance-related distress; dates or comparable photos if helpful. |
| Medicine | Start date, prescribed dose changes, missed doses, and all prescriptions, supplements, and nonprescription products. |
| Other changes | Illness, major stress, menstrual changes, alcohol or other substance use, and changes in routines. |
| Sleep and function | Sleep duration, daytime energy, concentration, work or school attendance, and withdrawal from usual activities. |
| Physical symptoms | Dizziness, fainting, unusual weakness, palpitations, confusion, or impaired coordination, with timing and severity. |
A symptom that follows a dose change is relevant information, not proof of a dose-dependent psychiatric effect. Likewise, waiting for acne to improve is not a reason to leave persistent depression or anxiety unassessed.
When to seek help
Contact your prescriber about new or persistent depression or anxiety, particularly if it disrupts sleep, relationships, work, or self-care. Depending on your symptoms, the assessment may include mental health questions, medication reconciliation, examination, or testing. PHQ-9 or GAD-7 questionnaires can support a clinical assessment; they do not identify which medicine caused symptoms or determine a dose change.
Seek urgent medical assessment for severe confusion, fainting, severe weakness, or an irregular heartbeat. If you have thoughts of self-harm or cannot stay safe, seek emergency assistance immediately. Do not wait to establish whether spironolactone is involved.
For non-emergency mood changes, ask the prescriber how to proceed rather than changing, tapering, or stopping treatment on your own.
Frequently asked questions
Can spironolactone cause depression?
A reliable acne-specific causal rate has not been established. New or persistent depression warrants assessment even when its cause is uncertain.
Does spironolactone cause anxiety?
Available acne evidence does not establish a controlled incidence of drug-caused anxiety. Report persistent symptoms and when they began.
What psychiatric or neurologic symptoms are in the label?
The label lists lethargy, mental confusion, ataxia, dizziness, headache, and drowsiness. These entries do not establish acne-specific depression or anxiety rates.[1]
How common are mood changes on spironolactone for acne?
There is no dependable percentage from the cited evidence. Acne-quality-of-life results and general adverse-event reports cannot supply that number.
Can clearing acne improve mood?
It may ease acne-related distress. Acne is associated with depression and anxiety, but clearing it does not guarantee mental health recovery.[4]
Should everyone get a PHQ-9 before starting?
The cited guideline overview does not establish that requirement. Discuss screening based on symptoms, mental health history, and clinical need.
Can fatigue be mistaken for depression?
Yes. Low energy can overlap with depression or have other causes. Persistent fatigue deserves assessment, especially with physical symptoms or impaired functioning.
Is spironolactone safe with lithium?
It can increase lithium toxicity risk. The combination needs prescriber oversight and periodic lithium monitoring; do not assume it is safe without review.[1]
Should I stop spironolactone if my mood changes?
Contact your prescriber for an individualized plan rather than stopping independently. Seek emergency assistance for self-harm thoughts or inability to stay safe.
Does a higher dose prove a higher mood risk?
No. The cited acne trial does not establish a psychiatric dose–risk curve. Symptoms after a dose change are worth reporting, but do not prove causation.
References
Sources checked October 14, 2026.
References
- DailyMed. Spironolactone tablets, film coated: prescribing information, updated March 12, 2026.
- American Academy of Dermatology. Acne clinical guideline overview, 2024.
- Santer M, et al. Effectiveness of spironolactone for women with acne vulgaris: SAFA randomized controlled trial. BMJ. 2023. PMID: 37192767.
- Samuels DV, et al. Acne vulgaris and risk of depression and anxiety: a meta-analytic review. 2020. PMID: 32088269.