Vaginal Progesterone in HRT: Understanding Uterine Protection
The estrogen dose, progesterone product and schedule all matter when vaginal progesterone is used in HRT. Systemic estrogen stimulates the uterine lining; adequate progestogen treatment provides protection. Studies of uterine uptake help explain vaginal delivery, while long-term trials test whether a particular regimen is sufficient.[4][5][7]
What the endometrial trials show
Estrogen can stimulate the uterine lining and cause hyperplasia. In the three-year PEPI trial, estrogen combined with studied progestogen regimens—including cyclic oral micronized progesterone—produced hyperplasia rates similar to placebo. PEPI did not test vaginal progesterone.[7]
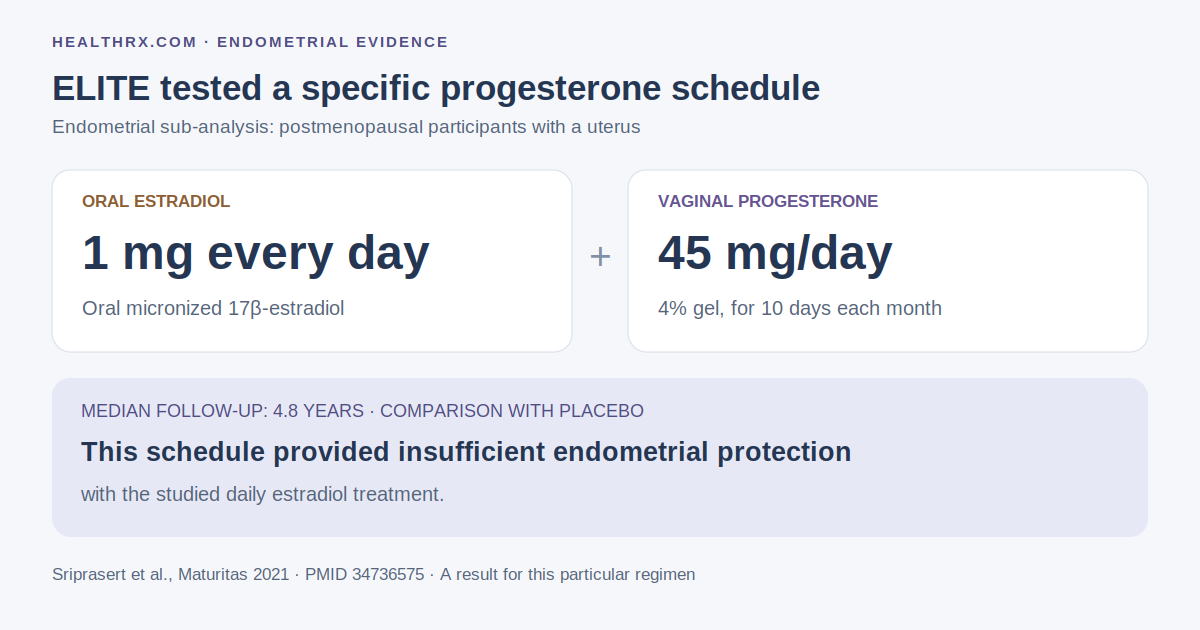
ELITE provides a direct warning about one vaginal regimen. Participants with a uterus received oral estradiol 1 mg daily plus 4% vaginal progesterone gel, 45 mg daily for 10 days each month, or placebo. Over a median 4.8 years, the hormone group had more endometrial thickening, biopsies and hyperplasia. Investigators concluded that this progesterone schedule did not fully oppose the estrogen.[4]
That finding does not establish that every vaginal regimen fails. It does mean this particular schedule should not be presented as proven protection. KEEPS used oral progesterone for 12 days monthly alongside oral or transdermal estrogen; its cardiovascular imaging results cannot validate a continuous vaginal schedule.[12]
Uterine uptake is only part of the answer
A small, short-term study found higher endometrial progesterone concentrations after vaginal dosing than after intramuscular dosing, despite higher blood levels with injections. This supports preferential uterine delivery. It did not establish a long-term menopause regimen or compare vaginal with oral dosing.[5]
Blood results also depend on formulation and measurement. In a 12-person postmenopausal study, Crinone 8% produced a higher peak progesterone concentration than oral Prometrium when measured by liquid chromatography–mass spectrometry. Another assay substantially overestimated levels after oral treatment.[6] Neither a serum result nor evidence of uterine uptake proves that a particular schedule prevents hyperplasia over years.
The exact product matters
These products have different formulations and labeled purposes. Their fertility or amenorrhea instructions should not be repurposed as menopause prescriptions.[1][2]
| Product | Progesterone content | Actual labeled purpose |
|---|---|---|
| Crinone 4% gel | 45 mg per applicator | Secondary amenorrhea |
| Crinone 8% gel | 90 mg per applicator | Progesterone supplementation or replacement in assisted reproduction for infertile women with progesterone deficiency; secondary amenorrhea when 4% fails |
| Endometrin vaginal insert | 100 mg per insert | Assisted-reproduction support for embryo implantation and pregnancy through 10 weeks in infertile women under 35 |
Neither label establishes a routine postmenopausal endometrial-protection regimen. A compounded capsule also cannot be assumed equivalent to either product.
Prometrium is labeled for oral use and contains peanut oil. Inserting its capsule vaginally changes the labeled route; its oral instructions do not validate vaginal interchangeability.[11] UK British Menopause Society guidance considers this option for oral intolerance, using similar doses and durations to oral treatment under limited evidence.[3]
Practical decisions and follow-up
Ask your prescriber to specify the product, estrogen exposure, progesterone schedule and bleeding follow-up. No single vaginal dose is established for every continuous combined HRT regimen. Choosing a patch rather than a gel does not resolve that evidence gap.
Crinone can cause residue, discharge or irritation. Its label requires at least six hours before or after another intravaginal treatment. Endometrin advises avoiding other vaginal products because their effects on progesterone release and absorption have not been assessed; a two-hour gap is not an established workaround.[1][2]
Report unexpected bleeding, especially heavy or prolonged bleeding, promptly. Assessment considers its timing, the actual regimen, adherence and individual risk factors. A reassuring ultrasound at one point does not prove that a progesterone schedule provides adequate long-term protection.[9]
Frequently asked questions
Do I need progesterone if I use an estradiol patch or gel?
An adequate progestogen plan is generally needed when systemic estrogen is used with a uterus present. Estradiol patches and skin gels are systemic products. The plan depends on the estrogen exposure and progesterone regimen.[7][11]
Can I insert a Prometrium capsule vaginally instead of swallowing it?
Ask your prescriber to specify the product and regimen before switching. Prometrium is labeled as an oral capsule and contains peanut oil; its oral instructions do not establish a vaginal dose conversion.[11]
What is the difference between Crinone gel and a compounded vaginal capsule?
Crinone is a labeled vaginal gel with specified strengths and release characteristics. A compounded capsule has its own formulation and cannot be assumed to deliver an equivalent dose or provide equivalent endometrial protection. Crinone's label itself does not establish a menopause protection regimen.[1]
Does vaginal progesterone cause drowsiness?
It can. Endometrin's patient information lists possible drowsiness. Vaginal delivery does not guarantee freedom from systemic effects, and products should not be assumed equally sedating. Avoid driving if you feel impaired.[2]
How long does vaginal progesterone take to work for endometrial protection?
There is no established onset time that guarantees protection. Absorption occurs before long-term protection can be assessed; adequacy depends on the complete estrogen–progesterone regimen. ELITE showed that uterine exposure alone did not make its tested schedule sufficient.[4][5]
Is vaginal progesterone safe for women with a history of breast cancer?
It is not proven safe for breast cancer survivors. Endometrin lists hormone-sensitive cancer, including breast cancer, as a contraindication. E3N's observational findings about progesterone-containing HRT do not establish vaginal-route safety or safety after breast cancer. Discuss systemic HRT with your oncology and menopause teams.[2][8]
Which estradiol formulation works best with vaginal progesterone?
The estrogen exposure and complete progesterone regimen guide the choice. KEEPS paired oral progesterone with oral or transdermal estrogen; it did not validate vaginal progesterone with either route.[12]
Can vaginal progesterone replace the need for a Mirena IUD in HRT?
An IUD and vaginal progesterone need different product and duration plans. Arrange ongoing endometrial protection with your prescriber before removing or replacing a device; IUD evidence cannot establish an equivalent vaginal dose.[3]
What dose of vaginal progesterone is used in a continuous combined HRT regimen?
The dose needs to fit the estrogen exposure and exact product. UK BMS guidance suggests similar doses and durations to oral progesterone when vaginal use is considered for oral intolerance, while acknowledging limited evidence.[3]
Will vaginal progesterone cause a period?
Cyclic treatment can cause withdrawal bleeding; continuous treatment can also cause spotting. Bleeding does not confirm adequate protection. Report unexpected bleeding, particularly if heavy or prolonged, rather than waiting automatically for six months.[9]
Can vaginal progesterone help with sleep or anxiety?
The small vaginal-versus-oral absorption study measured drug levels rather than sleep or anxiety benefits. Drowsiness can occur with vaginal progesterone and is not evidence of improved sleep quality.[2][6]
Is Divigel estradiol gel the same as a vaginal estrogen cream?
No. Divigel is systemic estradiol gel applied to upper-thigh skin for menopausal vasomotor symptoms. Do not insert it vaginally. Vaginal estrogen creams are separate products with their own indications and instructions.[10]
References
Sources checked October 14, 2026.
- Crinone prescribing information. DailyMed.
- Endometrin prescribing information. DailyMed.
- British Menopause Society. Progestogens and endometrial protection.
- Sriprasert et al. Endometrial effects of oral estradiol with vaginal progesterone in ELITE. 2021.
- Miles et al. Pharmacokinetics and endometrial tissue levels following intramuscular and vaginal progesterone. 1994.
- Levine H, Watson N. Comparison of the pharmacokinetics of Crinone 8% administered vaginally versus Prometrium administered orally in postmenopausal women. 2000.
- PEPI Trial. Effects of hormone replacement therapy on endometrial histology. 1996.
- Fournier et al. Unequal risks for breast cancer associated with different hormone replacement therapies: E3N. 2008.
- British Menopause Society. Management of unscheduled bleeding on HRT. 2024.
- Divigel prescribing information. DailyMed.
- Prometrium prescribing information. DailyMed.
- Harman et al. Arterial imaging outcomes and cardiovascular risk factors in KEEPS. 2014.