Metformin and GLP-1 Weight-Loss Results: Which Trials Can Be Compared?
A weight-loss number needs context: who entered the study, which medication they received, how long treatment lasted and how researchers analyzed the results. These details matter when comparing metformin with medications that act on GLP-1 pathways.
The evidence below includes one actual exenatide-versus-metformin trial and separate placebo-controlled obesity trials of semaglutide and tirzepatide. Tirzepatide is a dual GIP/GLP-1 receptor agonist. Those studies answer different questions, so their results cannot supply a head-to-head estimate for metformin versus semaglutide or tirzepatide.
What the studies actually compared
All doses below describe research exposures, not instructions for treatment. An estimand defines the treatment effect a trial aims to estimate, including how it handles events such as stopping treatment.
| Study and population | Duration and comparator | Weight result and units | Estimand or analysis boundary | Interpretation |
|---|---|---|---|---|
| DPP/DPPOS: adults without diabetes who had elevated fasting and postload glucose; 3,234 participants in the original DPP | DPP averaged 2.8 years; metformin 850 mg twice daily versus placebo, with a separate lifestyle group; later open-label follow-up | During DPP, mean weight loss was 2.06% with metformin versus 0.02% with placebo | Reported mean weight change; the original primary outcome was diabetes incidence | Shows modest average weight loss in a high-risk population; no GLP-1 comparator [1,2] |
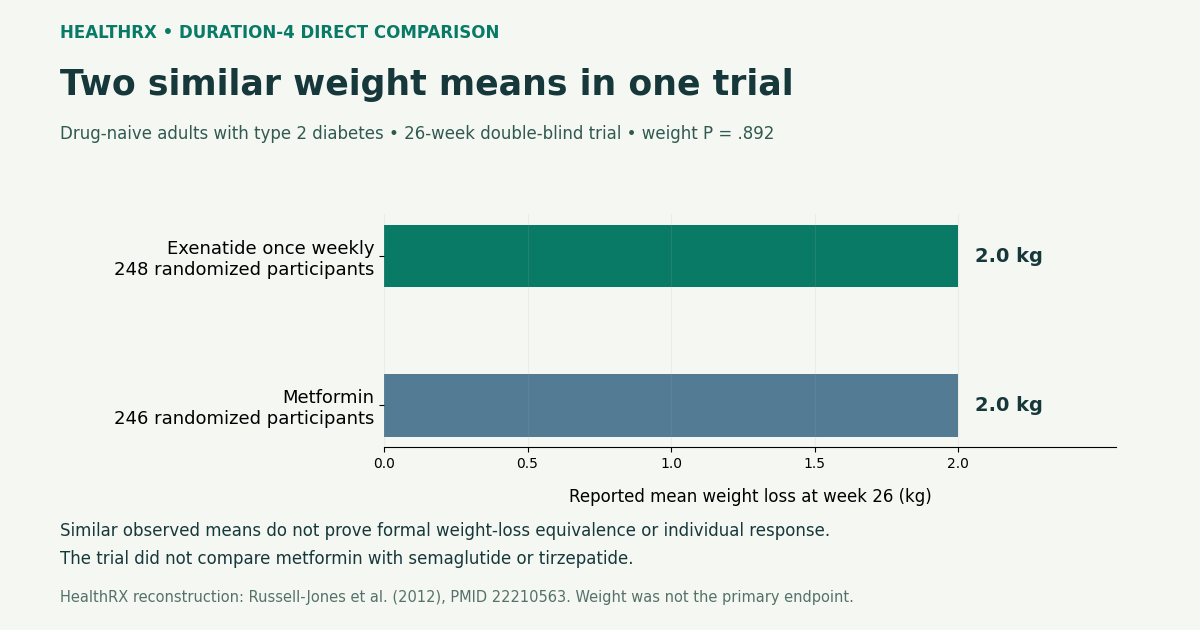
| DURATION-4: drug-naive adults with type 2 diabetes inadequately controlled by diet and exercise; 820 total | 26 weeks; exenatide 2 mg weekly, n=248, versus metformin up to 2,000 mg/day as tolerated, n=246; two additional drug arms | Mean change: −2.0 kg in each group; P=.892 | Secondary weight outcome; primary endpoint was HbA1c | Direct comparison, but similar observed means do not establish formal weight-loss equivalence [5] |
| STEP 1: 1,961 adults meeting overweight/obesity criteria, without diabetes | 68 weeks; semaglutide 2.4 mg weekly versus placebo; both groups received lifestyle intervention | Mean change: −14.9% versus −2.4% | Treatment-policy estimand, evaluating assignment regardless of treatment discontinuation or rescue intervention | Establishes benefit versus placebo in this population; no metformin group [3] |
| SURMOUNT-1: 2,539 adults meeting overweight/obesity criteria, excluding diabetes | 72 weeks, including 20-week escalation; tirzepatide versus placebo | In the 15 mg group: −20.9% versus −3.1% | Treatment-regimen estimand, evaluating assignment regardless of treatment discontinuation | Establishes benefit versus placebo; no metformin group [4] |
What the direct comparison tells us
DURATION-4 provides the actual randomized comparison between metformin and a GLP-1 receptor agonist in this set of studies. It tested once-weekly exenatide in people with type 2 diabetes. Participants received matching oral or injectable placebos to maintain blinding. [5]
At 26 weeks, both groups had an observed mean weight change of −2.0 kg. The weight comparison had a P value of .892. The primary endpoint was blood glucose control: HbA1c fell by 1.53 percentage points with exenatide and 1.48 with metformin, with P=.620. [5]
The weight finding does not prove equivalence or noninferiority for weight loss. It also cannot establish equal long-term results for individual patients. Exenatide is a different drug from semaglutide, and this diabetes population differs from those in STEP 1 and SURMOUNT-1. The older trial therefore does not overturn the obesity-trial findings.
Reading the larger obesity-trial numbers
In STEP 1, the treatment-policy difference between semaglutide and placebo was −12.4 percentage points, with a 95% confidence interval of −13.4 to −11.5. That is a comparison against placebo within STEP 1. It is not a measured advantage over metformin. [3]
SURMOUNT-1 reported a mean change of −20.9% in the tirzepatide 15 mg group under its treatment-regimen estimand. Substituting a figure from another analysis would change what the number represents. [4]
Neither trial supports subtracting the DPP metformin result to calculate a head-to-head drug effect. Differences in population, follow-up and analysis remain. Kilograms and percentages also cannot be interchanged without the relevant patient weights. These findings do not establish that every GLP-1 medication outperforms metformin in every setting.
What metformin's evidence means
The DPP's often-cited 31% reduction with metformin and 58% reduction with lifestyle intervention refer to relative reductions in diabetes incidence. They are not percentages of body weight lost. [1]
The DPPOS report described mean weight loss during DPP of 2.06% with metformin, with a standard deviation of 5.65%, versus 0.02% with placebo, with a standard deviation of 5.52%. Those standard deviations describe variability; they are not confidence intervals. The report included a two-year blinded phase followed by a seven- to eight-year open-label extension, with durability associated with adherence. [2]
When considering treatment, ask a clinician to reconcile the intended indication, actual product and applicable evidence with medical history, treatment goals and tolerability. Trial averages cannot promise personal weight loss. Cost comparisons also require dated dispensing and insurance-plan quotes: list price and out-of-pocket cost are different figures.
Frequently asked questions
How does metformin compare with GLP-1 medications for weight loss?
The direct DURATION-4 comparison found mean weight changes of −2.0 kg with both exenatide and metformin over 26 weeks in adults with type 2 diabetes. This did not establish formal weight-loss equivalence. Separate semaglutide and tirzepatide obesity trials showed substantial average losses versus placebo, but neither included metformin. They cannot provide a head-to-head estimate against it.
Can I take metformin and a GLP-1 drug at the same time?
Whether concurrent treatment is appropriate requires review of the indication, exact product, kidney function, other medications and tolerability. The studies summarized here do not establish a weight-loss benefit from adding one to the other. Ask your clinician to assess your existing regimen before making any change.
How much does metformin cost compared to GLP-1 drugs?
A useful comparison requires dated pharmacy dispensing quotes for the exact products and quantities, plus your plan's benefit information. Manufacturer list prices are different from what you pay out of pocket. Deductibles, copayments, coinsurance and any applicable assistance can change the final amount; these trials do not provide a current personal cost comparison.
Is metformin effective for weight loss in non-diabetic patients?
In DPP participants without diabetes who had elevated fasting and postload glucose, mean weight loss during DPP was 2.06% with metformin versus 0.02% with placebo. That supports modest average weight loss in this particular high-risk population. It does not establish the same response for everyone without diabetes.
Should I try metformin before a GLP-1 drug for weight loss?
These trials do not establish a required treatment sequence. Ask your clinician to reconcile your treatment indication, the actual product's evidence, medical circumstances, tolerability and access. A diabetes-prevention study and an obesity-treatment study may address different goals relevant to your care.
Does insurance cover GLP-1 medications for weight loss?
Coverage depends on the exact product, prescribed indication and current plan terms. Request a dated benefit determination describing formulary status, any authorization requirements and your expected out-of-pocket cost. A listed price or general statement about coverage cannot establish your eligibility or final expense.
Can metformin help with longevity even without diabetes?
These specific trials did not establish that metformin extends human lifespan. The DPP studied diabetes incidence, and its follow-up reported outcomes including weight and tolerability. Those findings do not demonstrate a longevity benefit for someone without diabetes.
References
- Knowler WC, Barrett-Connor E, Fowler SE, et al.; Diabetes Prevention Program Research Group. Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin. N Engl J Med. 2002.
- Diabetes Prevention Program Research Group. Long-term safety, tolerability, and weight loss associated with metformin in the Diabetes Prevention Program Outcomes Study. Diabetes Care. 2012.
- Wilding JPH, Batterham RL, Calanna S, et al.; STEP 1 Study Group. Once-Weekly Semaglutide in Adults with Overweight or Obesity. N Engl J Med. 2021.
- Jastreboff AM, Aronne LJ, Ahmad NN, et al.; SURMOUNT-1 Investigators. Tirzepatide Once Weekly for the Treatment of Obesity. N Engl J Med. 2022.
- Russell-Jones D, Cuddihy RM, Hanefeld M, et al.; DURATION-4 Study Group. Efficacy and safety of exenatide once weekly versus metformin, pioglitazone, and sitagliptin used as monotherapy in drug-naive patients with type 2 diabetes (DURATION-4): a 26-week double-blind study. Diabetes Care. 2012.