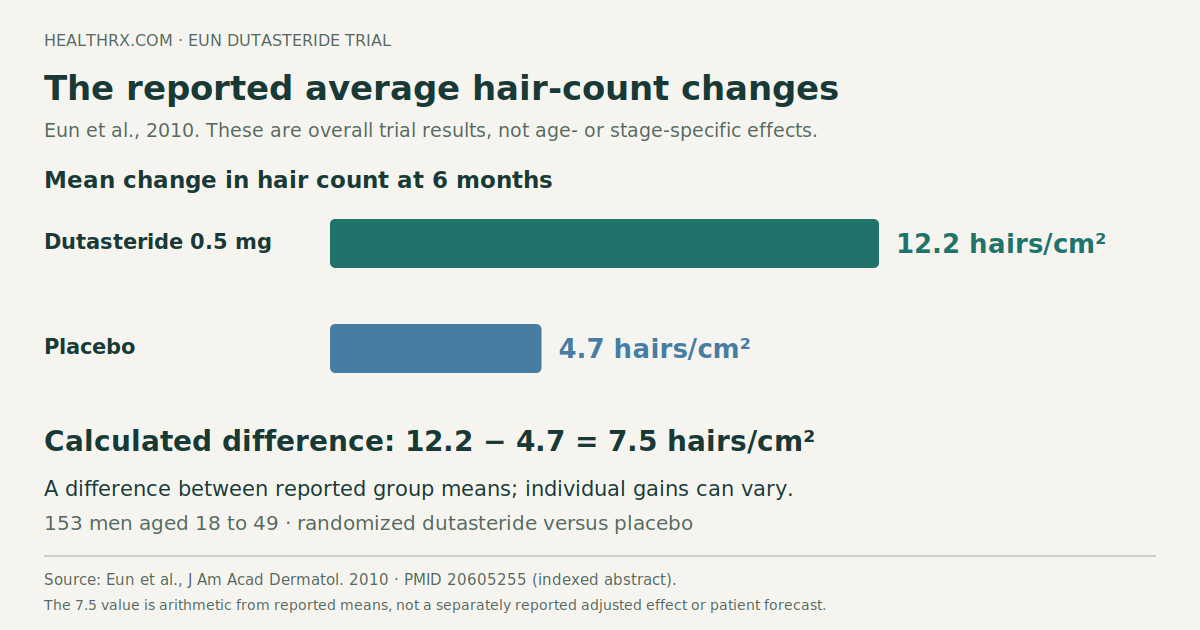Eun’s 2010 dutasteride trial: results and subgroup limits
Eun’s 2010 indexed abstract reports an overall hair-count benefit with dutasteride. It does not publish the age- or hair-loss-stage comparisons needed to say who responded best. A claim that younger men or a particular stage gained more needs evidence beyond this abstract.[1]
What the reported numbers mean
The study randomized 153 men aged 18 to 49 to dutasteride 0.5 mg daily or placebo for six months. Mean hair-count changes were 12.2 versus 4.7 hairs/cm², respectively, with P=.0319. Subtracting the reported means gives 7.5 hairs/cm². This is a calculated difference between group means; not an individual prediction or a separately reported adjusted effect. [1]
Individual outcomes can differ from the group mean. The reported average does not tell a reader how much hair they will gain.
What would establish a better-responding subgroup?
A difference between people at baseline is not evidence of a difference in treatment benefit. For example, finding different starting hair counts in younger and older men would not establish that dutasteride works better in either group.
The relevant comparison is the treatment-versus-control effect within each subgroup. Researchers would then compare those effects using an interaction estimate and its uncertainty. Looking only at improvement among treated participants leaves out what happened in the corresponding control groups.
The same reasoning applies to starting hair-loss severity, BMI, ethnicity, and DHT. A characteristic may describe participants without demonstrating that it predicts greater benefit. A useful subgroup claim needs comparative evidence, not simply a plausible explanation.
Keep the three trials separate
The three trials used different samples, comparator doses and hair-count reporting.[1][2][3]
| Trial | Sample and ages | Treatment arms | Duration | Endpoint or unit relevant here |
|---|---|---|---|---|
| Eun, 2010 [1] | 153 men, 18 to 49 | Dutasteride 0.5 mg; placebo | 6 months | Hair-count change in hairs/cm² |
| Gubelin Harcha, 2014 [2] | 917 men, 20 to 50 | Dutasteride 0.02, 0.1, or 0.5 mg; finasteride 1 mg; placebo | 24 weeks | Hair count in a target area 2.54 cm in diameter |
| Olsen, 2006 [3] | 416 men, 21 to 45 | Dutasteride 0.05, 0.1, 0.5, or 2.5 mg; finasteride 5 mg; placebo | 24 weeks | Hair-growth dose-response comparison |
In the 2014 study, dutasteride 0.5 mg improved hair count and width versus finasteride 1 mg. Its target-area count is not a count per square centimetre. It was a separate trial, not a 48-week extension of Eun. [2]
The 2006 research dose-response study used finasteride 5 mg, unlike the 2014 trial’s 1 mg arm. Its dutasteride 2.5 mg arm is not an individual treatment recommendation. [3]
Questions to take into a treatment discussion
Neither a higher research dose nor an average advantage over another drug supplies a personalized subgroup dosing rule. The AVODART prescribing information provides no DHT responder threshold or universal AGA subgroup-dose algorithm. [4]
Use the evidence to frame concrete questions:
- Is the proposed benefit an overall average or a demonstrated treatment-by-subgroup difference?
- Are the hair counts expressed per cm² or per target area?
- What outcome would be recorded to assess my response over time?
- What evidence supports the proposed dose or a switch from another medicine?
- What remains uncertain beyond six months, including long-term durability?
Frequently asked questions
Did younger men in the Eun trial respond better to dutasteride than older men?
Were there racial or ethnic subgroup analyses in this dutasteride AGA trial?
Does baseline hair loss severity predict response to dutasteride?
Was BMI analyzed as a subgroup variable in the Eun dutasteride trial?
Did sexual side effects differ by age subgroup?
Is 0.5 mg the right dutasteride dose for all AGA patient subgroups?
How long was the Eun dutasteride trial, and does 24 weeks capture full subgroup effects?
Can women use these subgroup findings to guide dutasteride use for hair loss?
Should clinicians check DHT levels before prescribing dutasteride based on this trial?
Does this trial support switching from finasteride to dutasteride?
References
- Eun HC et al. Efficacy, safety, and tolerability of dutasteride 0.5 mg once daily in male patients with male pattern hair loss: a randomized, double-blind, placebo-controlled, phase III study. J Am Acad Dermatol. 2010. DOI: 10.1016/j.jaad.2009.09.018. Source
- Gubelin Harcha W et al. A randomized, active- and placebo-controlled study of the efficacy and safety of different doses of dutasteride versus placebo and finasteride in the treatment of male subjects with androgenetic alopecia. J Am Acad Dermatol. 2014. Source
- Olsen EA et al. The importance of dual 5alpha-reductase inhibition in the treatment of male pattern hair loss: the results of a randomized placebo-controlled study of dutasteride versus finasteride. J Am Acad Dermatol. 2006. Source
- AVODART prescribing information. DailyMed. Revised October 2023; updated March 12, 2025. Source